
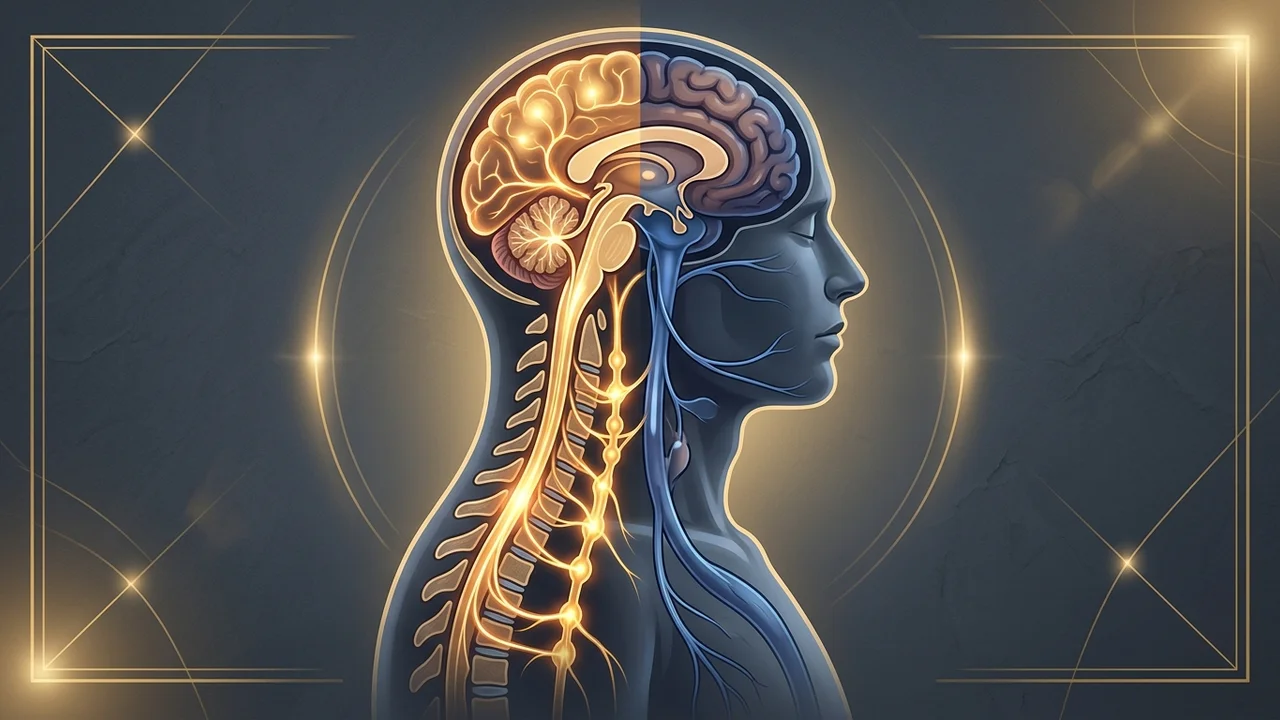
1. Defining Hypovigilance: The Flip Side of Chronic Threat
While hypervigilance represents a persistent elevation in sensory sensitivity and sympathetic motor readiness, hypovigilance is characterized by a pathological decrease in alertness, perceptual responsiveness, and autonomic output. Patients experiencing hypovigilance frequently report feeling "behind glass," struggling to track spoken conversations, experiencing sudden tunnel vision, or entering states of extreme psychomotor slowing even in environments that demand attention.
In evolutionary neurobiology, hypovigilance is not a malfunction; it is a conservative survival strategy. When an organism's sympathetic nervous system determines that neither active mobilization (fight) nor evasive locomotion (flight) can resolve an environmental threat or metabolic crisis, the autonomic architecture deploys its ancestral defense mechanism: systemic shutdown. Understanding the difference between hypervigilance and hypovigilance is crucial for clinicians and patients alike, as applying calming techniques designed for hyperarousal can paradoxically deepen a hypovigilant collapse.
2. The Neurobiology of the Autonomic Crash
The transition from hyperarousal to hypovigilance reflects a profound neurochemical and autonomic shift. During chronic fight-or-flight, the hypothalamic-pituitary-adrenal (HPA) axis and the locus coeruleus-norepinephrine (LC-NE) system operate at maximum capacity. Over time, central catecholamine stores become depleted, beta-adrenergic receptors desensitize, and the metabolic cost of sustaining high cardiac output becomes unsustainable.
At this critical threshold, the brainstem executes an autonomic emergency brake. The dorsal motor nucleus of the vagus nerve (DMNX)—the phylogenetically older, unmyelinated parasympathetic pathway—initiates massive inhibition of cardiorespiratory function. Heart rate drops rapidly, arterial blood pressure falls, cerebral perfusion decreases, and the brain enters a conservation-withdrawal posture.
Clinical Physiology Note: The Catecholamine Exhaustion Curve
In continuous telemetry assessments, patients shifting into hypovigilance exhibit marked low-frequency (LF) heart rate variability suppression paired with transient surges in high-frequency (HF) power. This indicates sudden parasympathetic co-activation rather than healthy vagal tone, producing severe subjective brain fog, muscle heaviness, and depersonalization.
3. Clinical Diagnostic Features: Hypervigilance vs. Hypovigilance
Because hypovigilance often manifests after an acute panic attack or intense period of work stress, it is frequently misdiagnosed as acute depression, chronic fatigue syndrome, or simple physical tiredness. The following clinical table outlines the differential presentation:
| Diagnostic Parameter | Hypervigilant State | Hypovigilant State (Crash) |
|---|---|---|
| Autonomic Dominance | Sympathetic Adrenergic Surge | Unmyelinated Dorsal Vagal (DMNX) |
| Heart Rate & BP | Tachycardia (>90 bpm), Elevated BP | Bradycardia or Labile Low BP, Orthostasis |
| Pupillary Dynamics | Mydriasis (Dilated), Rapid Saccades | Miosis or Fixed Vacant Gaze ("Thousand-Yard Stare") |
| Sensory Processing | Hyperacusis, Photophobia, Tactile Defense | Sensory Gating Failure, Muffled Audio, Tunnel Vision |
| Subjective Experience | "I am in imminent mortal danger" | "I am numb, exhausted, detached, and cannot care" |
4. Endogenous Opioids and Perceptual Blunting
One of the hallmark features of hypovigilance is stress-induced analgesia and emotional dissociation. When the autonomic nervous system shifts into dorsal collapse, the periaqueductal gray (PAG) in the midbrain stimulates the systemic release of endogenous opioids (dynorphins and beta-endorphins). These neuropeptides blunt pain receptors throughout the peripheral nervous system and inhibit neurotransmission in the anterior cingulate cortex and insular cortex.
While this mechanism protects the individual from overwhelming physical pain during lethal traumatic encounters, in modern chronic stress it produces a disorienting haze. Patients describe touching surfaces and barely feeling tactile texture, looking at loved ones and feeling zero emotional resonance, or finding themselves unable to muster motivation even for basic self-care tasks.
5. The Polyvagal Perspective: Dorsal Collapse
According to Polyvagal Theory formulated by Dr. Stephen Porges, autonomic responses follow a strict phylogenetic hierarchy. The ventral vagal complex (social engagement, vocal prosody, heart rate variability modulation) represents the most advanced evolutionary tier. Under perceived threat, ventral regulation retreats, uncovering the sympathetic mobilization system (hypervigilance). If sympathetic exertion fails to re-establish safety, the nervous system regresses to the oldest reptilian defense: dorsal vagal immobilization (hypovigilance).
In a hypovigilant collapse, gastrointestinal motility slows (potentially contributing to functional dyspepsia or gastroparesis), immune surveillance shifts, and metabolic expenditure is reduced to baseline essentials. This state is intimately linked to the wider continuum of dorsal vagal shutdown, where the body's survival program prioritizes metabolic preservation above social connection and cognitive processing.
6. Clinical Pacing: Safe Titration Out of Hypovigilance
Recovering from a hypovigilant episode requires a counterintuitive clinical strategy. Standard anxiety protocols—such as prolonged exhale breathing (4-7-8 ratio) or deep progressive muscle relaxation—can deepen dorsal vagal blunting by further depressing autonomic arousal. Instead, clinical neurophysiology emphasizes gentle, sensory-upward titration:
- Micro-Proprioceptive Activation: Lightly pressing the heels into the floor or slowly articulating the wrists to stimulate somatic mechanoreceptors without triggering sympathetic alarm.
- Orienting Visual Tracking: Moving the eyes and head deliberately across horizontal planes to re-engage cranial nerves III, IV, and VI alongside ventral vagal pathways.
- Thermal Titration: Splashing cool water on the wrists or drinking room-temperature water in measured swallows to re-establish interoceptive awareness.
- Vocal Prosody & Humming: Gentle phonation to activate the laryngeal recurrent branch of the vagus nerve and gently re-engage the nucleus ambiguus.