
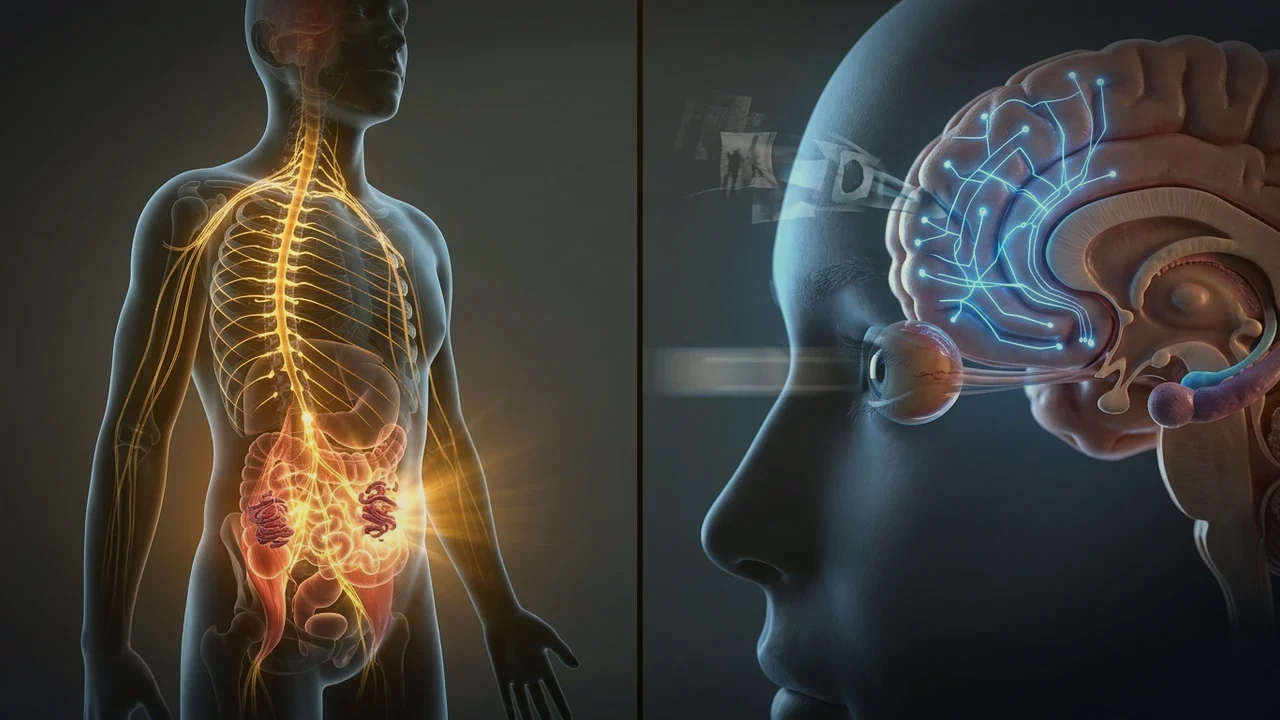
1. The Acoustic Startle Reflex: Millisecond Survival Circuitry
The acoustic startle reflex (ASR) is one of the most rapid motor responses in the human nervous system. Within 8 to 14 milliseconds of an unexpected acoustic transient exceeding 80 decibels, impulses travel from the auditory nerve into the nucleus reticularis pontis caudalis (PnC) in the pons. From the PnC, giant reticulospinal neurons project directly down the anterior horn of the spinal cord, commanding motor neurons across the face, neck, and limbs to contract instantaneously.
The evolutionary utility of this reflex is obvious: it ducks the head, blinks the eyelids to protect the corneas, and prepares flexor muscles for explosive evasive flight. However, in states of chronic allostatic stress, the threshold required to fire the PnC drops precipitously. The brainstem treats mundane environmental sounds—a closing car door, a colleague clearing their throat, or a dropped pen—as predatory attacks.
2. Pre-Pulse Inhibition (PPI) and Sensorimotor Gating
To prevent sensory overload, a healthy brain uses an automatic filtering mechanism known as pre-pulse inhibition (PPI). When a weak, non-startling sensory cue precedes a loud startling stimulus by 30 to 500 milliseconds, the central nervous system automatically dampens the subsequent motor startle response by up to 80%.
PPI is coordinated by the inferior and superior colliculi, the nucleus accumbens, and the pedunculopontine tegmental nucleus. In patients suffering from chronic stress, PTSD, or autonomic dysregulation, PPI breaks down. The brain loses its sensorimotor gating ability, meaning every single auditory event hits the reticular formation with raw, unbuffered force.
Neuro-Electrophysiological Finding: Electromyographic Blink Reflex
In electrophysiological testing, researchers measure startle magnitude via surface electromyography (EMG) of the orbicularis oculi muscle beneath the eye. Patients with depleted vagal tone demonstrate a twofold higher peak microvolt amplitude and prolonged latency recovery following standard 105 dB acoustic bursts compared to healthy controls.
3. Why Low Vagal Tone Magnifies Auditory Threat
What is the biological connection between heart rate variability (HRV), the vagus nerve, and jumpiness? The myelinated ventral vagal complex originates in the nucleus ambiguus of the medulla. Beyond regulating the sinoatrial node of the heart, the nucleus ambiguus shares dense inhibitory collaterals with the pontine reticular formation.
When vagal tone is robust, the vagal brake continually sends inhibitory GABAergic and cholinergic signals to the reticular core, keeping the startle threshold high. When vagal tone is chronically low—marked by depressed RMSSD on heart rate monitors—that tonic brake is absent. The reticular formation sits in a state of continuous hyperexcitability, ready to discharge at the slightest whisper of sensory fluctuation.
4. Autonomic Hypersensitivity and Nervous Overload
An exaggerated startle reflex rarely exists in isolation. It is usually the tip of the spear for systemic autonomic hypersensitivity and nervous overload, a condition where the central sensory processing networks lose their ability to habituate to repetitive stimuli.
- Sensory Cross-Modal Sensitization: Startle reactivity bleeds into other sensory modalities: sudden bright lights, unexpected gentle touch, or volatile odors trigger equal autonomic surges.
- Adrenal Exhaustion Cycle: Each startle spasm prompts immediate secretion of epinephrine from the adrenal medulla, creating a prolonged post-startle tremor and tachycardia that takes 20 to 45 minutes to subside.
- Postural Defense Lock: Repeated daily startle events keep the sternocleidomastoid, scalene, and trapezius muscles in permanent spasm, feeding into chronic myofascial neck and shoulder pain.
5. The Stapedius Muscle and Middle Ear Hyperacusis
Auditory startle is exacerbated by middle ear neuro-biomechanics. The stapedius muscle, innervated by the facial nerve (Cranial Nerve VII), tightens the stapes bone against the oval window to attenuate loud, low-frequency sounds. When ventral vagal and facial nerve tone drops, the stapedius becomes lax.
As a result, low-frequency environmental rumbles (air conditioning compressors, distant traffic, refrigerators) bypass natural acoustic filtering and slam into the cochlea at full amplitude. This produces subjective hyperacusis, where normal household environments feel painfully loud, keeping the brainstem in a state of uninterrupted acoustic siege.
6. Clinical Protocols for Recalibrating Sensory Thresholds
Re-establishing normal pre-pulse inhibition and raising the startle threshold requires targeted neuro-sensory reconditioning:
- Filtered Acoustic Desensitization: Listening to frequency-filtered acoustic inputs that progressively train the middle ear stapedius muscle to contract and filter low-frequency threat cues.
- Respiratory Sinus Arrhythmia Training: Practicing resonance frequency breathing (0.1 Hz, or approximately 5.5 to 6 breaths per minute) to directly elevate high-frequency heart rate variability and restore nucleus ambiguus reticular inhibition.
- Proprioceptive Deep Pressure Loading: Utilizing weighted lap pads or controlled isometric joint compression during sensory exposure to flood the dorsal column-medial lemniscal pathway, which exerts presynaptic inhibition on spinal startle interneurons.
- Vestibular Reset Drills: Controlled horizontal gaze stabilization drills (VOR exercises) to restore vestibulospinal balance and reduce reticular motor excitability.